Imagine having every textbook symptom of a severe yeast infection: thick white clumpy discharge in your underwear, raw vulvar redness, stinging when urine touches your skin (external dysuria), and painful friction during intimacy. You buy an over-the-counter box of miconazole (Monistat) or take a prescription tablet of oral fluconazole (Diflucan)—and within hours, the burning becomes ten times worse. Even more baffling, your gynecologist’s lab swab comes back completely negative for Candida, BV, and STIs.
When women search in desperation for “white clumpy discharge and burning but negative yeast test and Monistat made it worse,” the answer is frequently an under-recognized condition called Cytolytic Vaginosis (CV)—originally termed Döderlein’s cytolysis in peer-reviewed NIH/PubMed gynecological literature.
As part of our Intimate & Vaginal Health diagnostic series, this guide explains how to distinguish Cytolytic Vaginosis from Vulvovaginal Candidiasis (Yeast) and Bacterial Vaginosis using a simple 10-second pH test, cycle tracking, and calibrated microbiome modulation.
Clinical Key Takeaways: Cytolytic Vaginosis vs. Yeast Infection
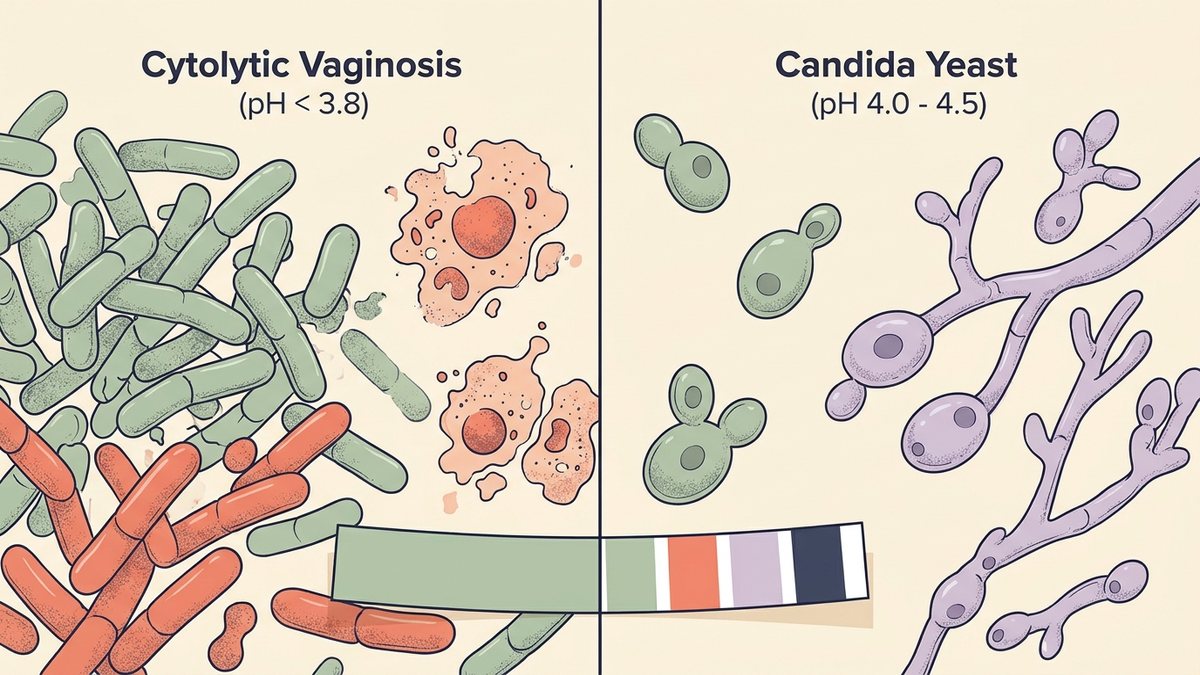
- The Great Clinical Impersonator: Cytolytic Vaginosis (CV) occurs when excessive Lactobacillus overgrowth hyper-acidifies the vagina (pH < 3.5–3.8). The extreme lactic acid concentration literally dissolves (lyses) intermediate squamous epithelial cells, producing thick, white, clumpy discharge and intense vulvar burning that looks identical to a yeast infection.
- Why Monistat & Diflucan Fail: Because CV is caused by bacterial hyper-acidity—not Candida fungi—azole antifungals completely fail, and topical creams often worsen the chemical burning on raw, lysed tissue.
- 2 Tell-Tale Clues: (1) Your symptoms peak the week before your period (luteal phase) and miraculously vanish during your period (because menstrual blood at pH 7.4 buffers the acid), and (2) an at-home vaginal pH strip reads 3.5 or lower with a negative fungal culture.
What Is Cytolytic Vaginosis? When “Good” Lactobacillus Bacteria Overgrow
Throughout women’s health education, we are taught that Lactobacillus bacteria are the heroes of the vaginal microbiome. And in 90% of scenarios, that is true: lactobacilli maintain a protective acidic pH between 3.8 and 4.5 that prevents pathogens from taking hold.
However, biology always operates within a homeostatic window. In Cytolytic Vaginosis, certain high-acid-producing Lactobacillus strains multiply to extreme concentrations, driving intravaginal pH down to 3.0 to 3.8 and flooding the mucosa with concentrated lactic acid, hydrogen peroxide, and proteolytic enzymes.
Why Does Hyper-Acidity Create “Cottage Cheese” White Clumps?
Under normal conditions, your vaginal walls shed superficial squamous cells smoothly—part of the natural physiological vaginal discharge cycle. When vaginal pH drops below 3.8, the excessive acidity chemically erodes and ruptures (lyses) the cell membranes of intermediate squamous epithelial cells. What looks like thick, white, pasty or curd-like “yeast” discharge in Cytolytic Vaginosis is actually millions of shredded, sloughed vaginal skin cells and cytoplasmic fragments mixed with overgrown lactobacilli.
Because the underlying mucosal barrier has been stripped raw by acid lysis, urine touching the vestibule causes immediate stinging, and applying chemical antifungal creams or boric acid suppositories pours fuel on the fire.
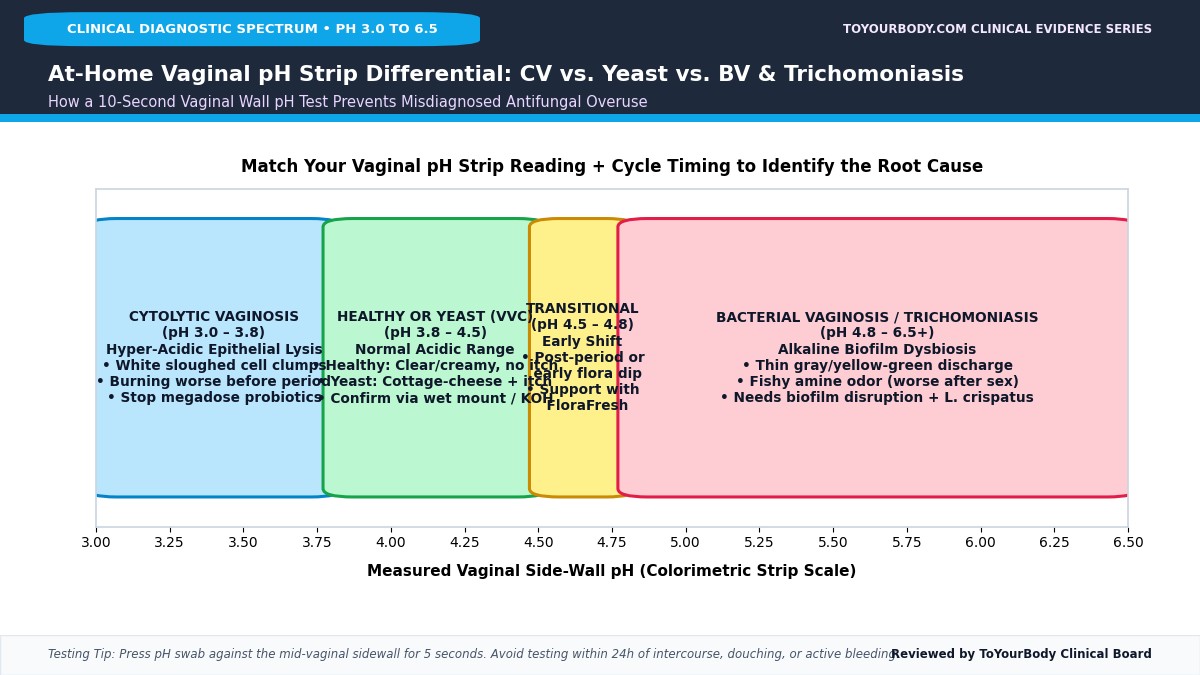 Figure 2: Vaginal side-wall pH diagnostic spectrum distinguishing hyper-acidic Cytolytic Vaginosis (pH 3.0–3.8) from Yeast (pH 4.0–4.5) and BV (pH 4.8–6.5).
The Luteal Phase & Menstrual Clue: Why CV Stops During Your Period
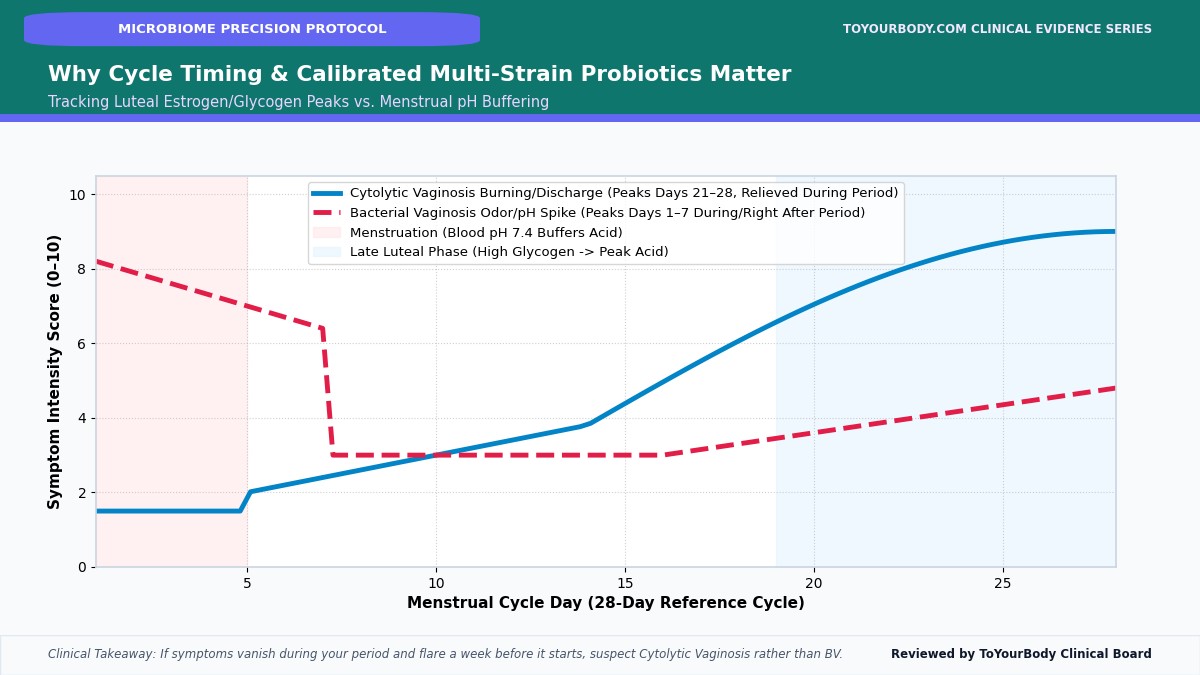
One of the sharpest clinical clues separating Cytolytic Vaginosis from candida white discharge and itching or Bacterial Vaginosis is how your symptoms behave across your 28-day menstrual cycle:
- Days 12–16 (Ovulation): Discharge is typically normal clear, stretchy egg-white mucus (cervical pH ~7.0).
- Days 19–28 (Late Luteal Phase Peak): High luteal estrogen and progesterone pack the vaginal epithelium with intracellular glycogen. Overgrown lactobacilli gorge on this glycogen surge, pumping out massive amounts of lactic acid. Burning, itching, and thick white cellular clumps reach peak intensity 3 to 7 days before your period starts.
- Days 1–5 (Menstruation Relief): The moment menstrual bleeding begins, alkaline blood (pH 7.4) flows through the vaginal canal, naturally buffering the excess acid. Women with Cytolytic Vaginosis almost universally report that their burning vanishes during their period—only to build back up two weeks later! (By contrast, BV typically worsens during and right after menstruation, as explained in our post-period pH balance guide.)
Differential Diagnosis Table: Cytolytic Vaginosis vs. Yeast Infection (VVC) vs. Bacterial Vaginosis (BV)
| Diagnostic Feature | Cytolytic Vaginosis (CV) | Yeast Infection (Candidiasis) | Bacterial Vaginosis (BV) |
|---|---|---|---|
| Vaginal Wall pH | Hyper-Acidic: pH 3.0 – 3.8 | Normal Acidic: pH 4.0 – 4.5 | Alkaline Shift: pH 4.8 – 6.0+ |
| Discharge Texture | Thick white pasty/clumpy (sloughed skin cells) | Thick white cottage-cheese curds | Thin, homogeneous milky-white or grayish |
| Vaginal Odor | Odorless or sharply sour/vinegar-like | Odorless or faintly bread/yeast-like | Distinct “fishy” amine odor (worse after sex) |
| Cycle Timing | Worse 1 week before period; stops during period | Can flare pre-period or after antibiotics | Worse during & immediately after period |
| Saline Wet Mount Microscopy | Abundant lactobacilli, bare nuclei, fragmented epithelial cytoplasm, few WBCs, no hyphae | Budding yeast blastospores & pseudohyphae on 10% KOH prep; elevated WBCs | >20% Clue cells (stippled epithelial borders), absent lactobacilli, positive KOH whiff |
| Response to Monistat / Diflucan | Fails completely (topical creams often burn worse) | Resolves within 3–7 days (for C. albicans) | No improvement; requires biofilm + flora protocol |
Clinical Recovery Protocol: How to Calm Cytolytic Vaginosis & Rebalance Safely
1. Pause Uncalibrated Megadose Single-Strain Probiotics & Antifungals Immediately
Many women develop Cytolytic Vaginosis after weeks of stacking multiple high-CFU (50–100 billion CFU) generic gut probiotics, inserting homemade yogurt, or repeatedly applying OTC antifungal creams and lactic acid gels without checking their pH. If your vaginal pH is below 3.8 and your fungal swab is negative, stop all antifungals, vinegar washes, lactic acid gels, and uncalibrated megadose probiotics for 2 to 3 weeks.
2. Short-Term External Sodium Bicarbonate Sitz Baths (To Buffer Acute Acid Lysis)
In peer-reviewed gynecological protocols for confirmed Cytolytic Vaginosis, gently raising the external vestibular and introital pH out of the hyper-acidic <3.5 zone stops epithelial cell shredding:
- Dissolve 2 to 4 tablespoons of pure sodium bicarbonate (baking soda) in a shallow basin or sitz bath of warm water.
- Soak the external vulva for 15 to 20 minutes once or twice daily for 7 to 10 days during your luteal flare. (Avoid high-pressure internal baking soda douches, which can over-correct and trigger BV.)
3. Transitioning from Uncalibrated Megadoses to Precision Microbiome Balance
What happens if you swing like a pendulum between hyper-acidic irritation before your period and high-pH BV odor after your period? That pattern indicates microbiome instability rather than steady homeostasis. Instead of flooding the vaginal canal with harsh direct acidifiers or 100-billion-CFU generic gut capsules, use a pH strip first—and when supporting your microbiome after antibiotics, periods, or intimacy, rely on a calibrated, physiologically balanced formula.
Precision Over Megadosing: Calibrated Vaginal Microbiome Support
When your vaginal pH strip confirms an alkaline shift (>4.5 after menstruation, antibiotics, or unprotected sex) or when you are rebuilding after a vaginal suppository reset, avoid uncalibrated single-strain megadoses. Wellness Nest FloraFresh provides a targeted, physiological blend of Lactobacillus crispatus, L. rhamnosus, and L. reuteri paired with cranberry proanthocyanidins—designed to support the natural 3.8–4.5 homeostatic zone via the gut–vaginal axis without harsh local chemical irritation.
Read our full FloraFresh Clinical Review or compare all verified formulas in our Women’s Health Products Hub.
Frequently Asked Questions (Clinician-Reviewed FAQ)
How can I tell Cytolytic Vaginosis apart from a yeast infection at home?
While a saline wet mount under a microscope is the clinical gold standard, two at-home indicators strongly point to Cytolytic Vaginosis: (1) a vaginal pH strip reading 3.5 or lower alongside negative yeast cultures, and (2) burning and white clumpy discharge that worsen after Monistat/Diflucan but disappear during menstrual bleeding.
Does boric acid cure Cytolytic Vaginosis?
No. Boric acid is indicated for high-pH Bacterial Vaginosis biofilms and azole-resistant Candida glabrata. In Cytolytic Vaginosis, your vaginal epithelium is already raw and lysed from excess acid; inserting boric acid will increase vulvovaginal burning.
Step-by-step clinical decoder calibrated against ACOG, CDC & NIH thresholds. Answer each quick step for your tailored protocol.
Alkaline Amine Volatilization & L. crispatus Depletion
When alkaline semen (pH 7.1–8.0) or menstrual blood (pH 7.4) buffers vaginal lactic acid above pH 4.7, anaerobic Gardnerella vaginalis biofilms release volatile polyamines (fishy odor). If you recently used 600mg boric acid or antibiotics, bare vaginal mucosa will relapse within 2–3 weeks unless actively reseeded.
Recommended Clinical Guides for Your Pattern:- 24-Hour Vaginal pH Reset After Sex & Period (pH 3.8–4.5)
- 600mg Boric Acid Biofilm Protocol + When to Switch to Probiotics
- Evidence-Based Natural Remedies for Recurrent BV
- Cytolytic Vaginosis (pH < 3.8) vs. Yeast Infection • OTC Yeast Guide • White Discharge & Itching
Replenishes human-adapted Lactobacillus crispatus and L. rhamnosus via the gut–perineal axis to produce D/L-lactic acid and lock vaginal pH at 3.8–4.5.
Check FloraFresh Availability at Wellness Nest →Luteal / Perimenopausal Allopregnanolone Drop & 3 AM Cortisol Rebound
Declining progesterone deprives your brain’s GABAA receptors of calming allopregnanolone while narrowing your hypothalamic thermoneutral zone. Between 2:00 AM and 4:00 AM, a subtle hepatic glycogen dip triggers an unbraked adrenal cortisol and adrenaline surge that jolts you awake.
Tonight’s Clinical Recovery Protocol:- Progesterone–GABA Drop & Non-Hormonal Luteal/Perimenopause Sleep Fix
- Why Do I Wake Up at 3 AM in Menopause? (Cortisol & Glycemic Shield)
- Cooling Hypothalamic KNDy Neurons & Night Sweats Relief
- Magnesium Glycinate vs. L-Threonate & Thermal Dumping Protocol
Stabilizes estrogen recirculation via the gut estrobolome, calms overactive KNDy hot-flash neurons, and blunts 3 AM cortisol awakenings without synthetic hormones.
Check MenoMate Price & Bundles at Wellness Nest →Enterohepatic Estrobolome Dysregulation & HPA Visceral Storage
When gut β-glucuronidase activity is disrupted alongside elevated HPA-axis cortisol, estrogen recirculation becomes erratic—starving vaginal Lactobacillus crispatus of glycogen (triggering pH shifts), destabilizing nocturnal thermoregulation (3 AM waking), and activating abdominal glucocorticoid receptors (cortisol belly).
Your 3-Pillar Clinical Reading Plan:- The Estrobolome & Gut–Vaginal Axis: Connecting BV, 3 AM Sleep & Belly Fat
- Cortisol Belly & Menopause Weight Gain: Visceral Fat Reset
- Fixing the “Tired But Wired” Diurnal Cortisol Curve
- Post-Lunch Bloating & Gut Microbiome Enzyme Guide
Coordinating L. crispatus urogenital colonization (FloraFresh) with intestinal β-glucuronidase and HPA-cortisol modulation (MenoMate) addresses all three concentric pillars simultaneously.