Where is the G-spot and what does it feel like? Rather than an isolated “magic button,” modern 3D pelvic ultrasound shows that the Gräfenberg spot (G-spot) is an anatomical crossroads located 1.5 to 2.5 inches (4–6 cm) inside the vagina along the upper (anterior) wall—directly toward the belly button behind the pubic bone. Physically, it feels noticeably rougher and more ridged (like the roof of your mouth or a walnut shell) than the smooth side walls of the vagina, and swells into a firm, spongy cushion during arousal.
- The Clitourethrovaginal (CUV) Complex: Internal G-spot pressure stimulates the internal legs (crura) and vestibular bulbs of the clitoris, the urethral sponge, and the paraurethral Skene’s glands simultaneously.
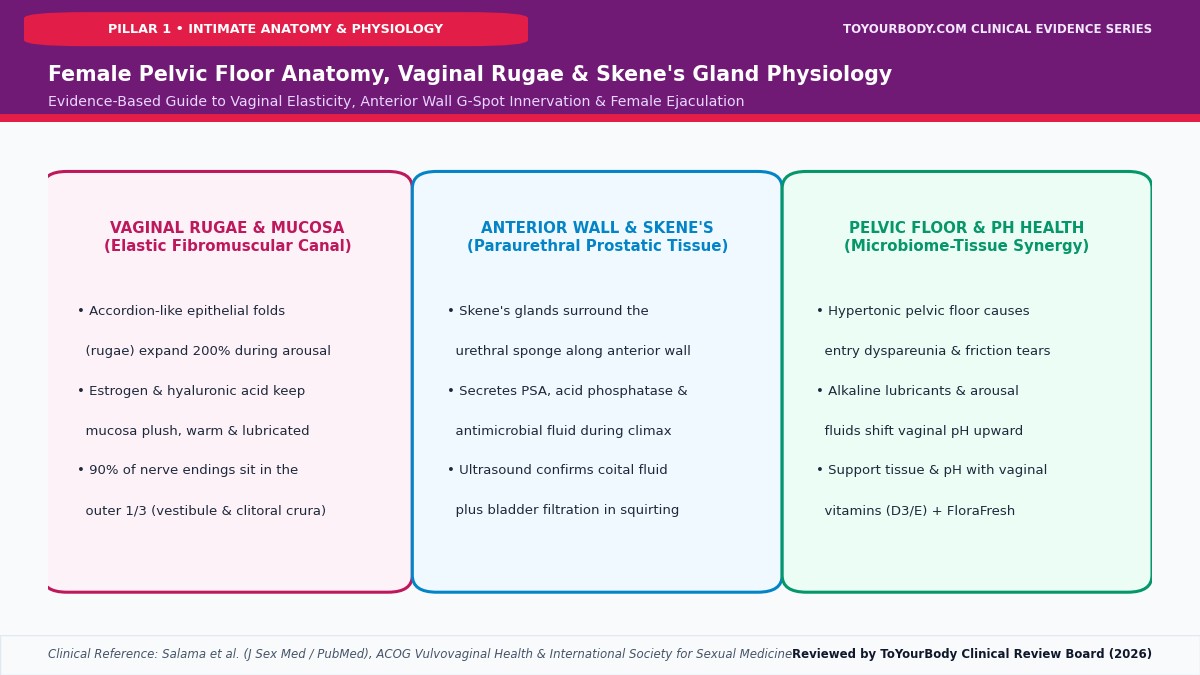
- Why angle matters more than depth: Over 90% of vaginal sensory nerve endings sit in the outer one-third of the canal and along the anterior wall—not deep near the cervix.
Why the “G-Spot vs. Clitoris” Debate Was Solved by Pelvic Ultrasound
For decades, anatomists argued over whether the G-spot was a distinct organ or a myth, while women wondered why straight in-and-out penetration rarely produced the same sensation as targeted anterior-wall pressure. High-frequency dynamic sonography and pelvic MRI studies (led by researchers such as Dr. Helen O’Connell and Dr. Emmanuele Jannini) resolved the controversy by mapping the clitourethrovaginal (CUV) complex.
What most people call “the clitoris” is only the external glans—a pea-sized bundle of 8,000+ nerve endings at the top of the vulva. Beneath the surface, the clitoris is a wishbone-shaped erectile structure extending 9 to 11 centimeters internally. Its two erectile legs (crura) and paired vestibular bulbs wrap directly around the urethra and hug the upper (anterior) wall of the vagina. When you press upward against the G-spot zone inside the vagina, you are pressing directly against the internal root of the clitoris and the Skene’s gland tissue surrounding the urethra.
Exactly Where to Find the G-Spot & What Its Texture Feels Like
If you have read our clinical guide on what the inside of a vagina feels like, you know that the vaginal canal is a muscular fibromuscular tube lined with accordion-like transverse folds called vaginal rugae. However, the texture is not uniform:
- Depth (1.5 to 2.5 Inches Inside): Insert a clean, lubricated finger about halfway to the second or third knuckle, curving your fingertip upward toward the ceiling (or toward the navel when lying on your back).
- Distinct Walnut-Like Ridges: While the back (posterior) wall and sides of the vagina feel relatively smooth and elastic, the anterior wall directly behind the pubic bone has prominent, firm, bumpy transverse ridges—similar in texture to the hard palate on the roof of your mouth or the surface of a walnut.
- Arousal Engorgement: Before arousal, this area may feel flat or simply sensitive. After 5 to 10 minutes of clitoral and emotional arousal, nitric oxide increases pelvic blood flow, causing the urethral sponge and Skene’s tissue to swell into a distinct, pillowy mound.
Anatomical Comparison: External Clitoral Glans vs. Internal G-Spot (CUV Complex) vs. Anterior Fornix
| Anatomical Zone | Location & Depth | Primary Nerve Supply | Typical Sensation & Response |
|---|---|---|---|
| External Clitoral Glans | External apex of the inner labia beneath the clitoral hood | Dorsal nerve of the clitoris (branch of pudendal nerve) | Sharp, electric, fast-building tactile pleasure; requires indirect or well-lubricated touch. |
| G-Spot / CUV Complex | 1.5–2.5 inches inside along the upper (anterior) vaginal wall | Pelvic splanchnic, hypogastric & cavernous nerves | Deep, warm pressure; initial urge-to-pee sensation shifting into full-body contractions & Skene’s fluid release. |
| Anterior Fornix (“A-Spot”) | 4–5 inches deep in the pocket just in front of the cervix | Uterovaginal plexus & vagus nerve projections | Smooth tissue; triggers rapid vaginal lubrication and deep visceral warmth without urethral pressure. |
Why Pelvic Floor Tone and Mucosal Health Determine Internal Sensation
Two physiological factors strongly influence how pleasurable internal anterior-wall stimulation feels:
- Pelvic Floor Balance (Avoiding Hypertonicity): While moderate pelvic floor strength (see our muscle strengthening guide) increases orgasmic blood flow, a chronically clenched or hypertonic pelvic floor—often triggered by high cortisol and stress (see systematic relaxation)—causes deep pain or burning during G-spot contact.
- Healthy Glycogen-Rich Epithelium & pH 3.8–4.5: Estrogen and a thriving Lactobacillus crispatus microbiome keep the anterior vaginal rugae plump, elastic, and resilient against friction. When vaginal pH rises above 4.5 or subclinical inflammation is present, internal pressure feels raw or irritating instead of pleasurable (learn why burning happens after sex). Supporting your urogenital microbiome with clinically studied oral probiotics (Wellness Nest FloraFresh Review) helps maintain supple, irritation-free mucosal tissue.
Step-by-step clinical decoder calibrated against ACOG, CDC & NIH thresholds. Answer each quick step for your tailored protocol.
Alkaline Amine Volatilization & L. crispatus Depletion
When alkaline semen (pH 7.1–8.0) or menstrual blood (pH 7.4) buffers vaginal lactic acid above pH 4.7, anaerobic Gardnerella vaginalis biofilms release volatile polyamines (fishy odor). If you recently used 600mg boric acid or antibiotics, bare vaginal mucosa will relapse within 2–3 weeks unless actively reseeded.
Recommended Clinical Guides for Your Pattern:- 24-Hour Vaginal pH Reset After Sex & Period (pH 3.8–4.5)
- 600mg Boric Acid Biofilm Protocol + When to Switch to Probiotics
- Evidence-Based Natural Remedies for Recurrent BV
- Cytolytic Vaginosis (pH < 3.8) vs. Yeast Infection • OTC Yeast Guide • White Discharge & Itching
Replenishes human-adapted Lactobacillus crispatus and L. rhamnosus via the gut–perineal axis to produce D/L-lactic acid and lock vaginal pH at 3.8–4.5.
Check FloraFresh Availability at Wellness Nest →Luteal / Perimenopausal Allopregnanolone Drop & 3 AM Cortisol Rebound
Declining progesterone deprives your brain’s GABAA receptors of calming allopregnanolone while narrowing your hypothalamic thermoneutral zone. Between 2:00 AM and 4:00 AM, a subtle hepatic glycogen dip triggers an unbraked adrenal cortisol and adrenaline surge that jolts you awake.
Tonight’s Clinical Recovery Protocol:- Progesterone–GABA Drop & Non-Hormonal Luteal/Perimenopause Sleep Fix
- Why Do I Wake Up at 3 AM in Menopause? (Cortisol & Glycemic Shield)
- Cooling Hypothalamic KNDy Neurons & Night Sweats Relief
- Magnesium Glycinate vs. L-Threonate & Thermal Dumping Protocol
Stabilizes estrogen recirculation via the gut estrobolome, calms overactive KNDy hot-flash neurons, and blunts 3 AM cortisol awakenings without synthetic hormones.
Check MenoMate Price & Bundles at Wellness Nest →Enterohepatic Estrobolome Dysregulation & HPA Visceral Storage
When gut β-glucuronidase activity is disrupted alongside elevated HPA-axis cortisol, estrogen recirculation becomes erratic—starving vaginal Lactobacillus crispatus of glycogen (triggering pH shifts), destabilizing nocturnal thermoregulation (3 AM waking), and activating abdominal glucocorticoid receptors (cortisol belly).
Your 3-Pillar Clinical Reading Plan:- The Estrobolome & Gut–Vaginal Axis: Connecting BV, 3 AM Sleep & Belly Fat
- Cortisol Belly & Menopause Weight Gain: Visceral Fat Reset
- Fixing the “Tired But Wired” Diurnal Cortisol Curve
- Post-Lunch Bloating & Gut Microbiome Enzyme Guide
Coordinating L. crispatus urogenital colonization (FloraFresh) with intestinal β-glucuronidase and HPA-cortisol modulation (MenoMate) addresses all three concentric pillars simultaneously.